


· Executive Brief
National Immunization Awareness Month 2026
Move beyond reminders by reviewing how the organization prevents, detects, responds, and learns.

Leadership signal
Use National Immunization Awareness Month to examine the system behind the message.
Campaign messages can raise attention, but operating reliability depends on what happens before, during, and after a concern. Leaders can map ownership, approved prevention practices, readiness checks, escalation, documentation, and the route used to learn from exceptions.
Start by distinguishing what is known from what the organization still needs to learn. A campaign plan, communication volume, or meeting count does not establish that a route is usable. Leaders need direct listening, clear ownership, locally defined measures, and a method for keeping exceptions visible.
Executive opening
Immunization coverage is an operating system, not a campaign
Vaccines only protect people who receive them on time, and that depends on systems that find, remind, reach and record. When those systems weaken, outbreaks follow the gaps. During a 2025 measles outbreak, the New Mexico Department of Health reported 99 outbreak-related cases, approximately one half of them in adults.[13] The state’s response combined a centralized webpage, a telephone helpline and mobile vaccination clinics.[13]
The research gathered for this brief shows that the most reliable gains come from combining routine tools rather than relying on a single message. In a cluster randomized trial at 6 primary care practices, parent reminder-recall plus clinician audit and feedback raised HPV vaccine receipt to 39.7%, compared with 21.9% under usual care.[15] Pharmacy-based interventions nearly doubled vaccination uptake in pre-post comparisons among vulnerable adults.[5]
Gains are not shared equally. A secondary analysis of the same HPV trial found the multilevel intervention had limited effect for children living in the areas of highest deprivation.[14] A pilot trial in safety-net clinics serving historically Black neighborhoods found that digital stories reached only 7% of caregivers, even though vaccination improved.[1] Equity needs its own design work, not just a larger version of the usual outreach.
This brief adds the research base to the executive guidance already on this page. It covers burden and measurement, the continuum from reminder to recorded dose, access through schools, pharmacies and mobile outreach, equity and trust, the immunization workforce and public communication. Each section separates what studies found from what leaders may choose to do. None of it is individual medical advice. Leaders can use it to choose one immunization handoff to strengthen first, and to decide which measure will show whether the change held.
Current evidence
What the research says about reminders, recall and measurement
Reminder-recall is one of the best-tested immunization tools, and the trials show both its value and its limits. In the Minnesota HPV trial of 9,242 children aged 11 and 12, parent reminder-recall alone produced vaccine receipt of 34.6%, and clinician audit and feedback alone produced 30.4%.[15] Compared with usual care, the odds of vaccination were higher for reminder-recall, with an odds ratio of 1.56, and for the combination, with an odds ratio of 2.03.[15] Audit and feedback alone did not differ significantly from usual care.[15]
Registry-based recall at city scale shows a small but real effect. New York City’s immunization registry sent a generic text message urging annual influenza vaccination to parents of children who had not yet been vaccinated.[2] Of the messages sent, 73% were delivered successfully.[2] Within 28 days, 4.7% of children aged 15 months to 4 years in the text group were vaccinated, compared with 4.3% of controls, a risk ratio of 1.095.[2]
Message content and audience matter. In a Denver pilot trial of 200 children, caregivers received texts linking to digital stories that centered Black families.[1] At the February 2025 influenza peak, 62% of intervention children remained unvaccinated, compared with 74% under usual care.[1] Children of intervention caregivers were more likely to be vaccinated, with an adjusted hazard ratio of 1.63, though story reach was low.[1]
Coverage measurement is a prerequisite for targeting. In southern Madagascar, 3,975 trained community health workers verified the vaccination status of all children younger than 5 years in targeted communities.[12] Overall, 58% of the 368,227 children enumerated had no documented dose of diphtheria-tetanus-pertussis vaccine.[12] District-level prevalence of no-dose children ranged from 25% to 86%, and those data guided mapping and targeted outreach.[12]
The same lesson applies in high-income settings with mature registries. In Australian residential aged care homes, publicly available register data showed the proportion of homes achieving at least 80% influenza vaccination coverage rose from 29% in 2024 to 64% in 2025.[4] Managers and pharmacists interviewed in that study named access to comprehensive data as one of five key themes.[4] The authors also called for improved register reporting functionality to sustain those gains.[4] For health systems, the equivalent question is whether the registry and the electronic record can produce a reliable list of who is due, by clinic and by neighborhood, at any time.
Figure 1
Combining tools reaches more people than any single message
Percent of eligible children or facilities reaching the reported vaccination outcome. Values are copied from the cited studies [3], [4], [15]; none is estimated.
Data note. The three HPV bars come from one trial and can be compared directly; the school and aged care bars come from different studies, populations and measures, so comparison with them is indirect.
Limitation. The aged care value is a share of facilities rather than people, and its rise could not be attributed to one program.
Figure data (5 rows)
| Measure | Value | Population, setting and year as reported | Source |
|---|---|---|---|
| HPV vaccine dose received, usual care | 21.9% | Children aged 11 and 12 at 6 primary care practices in southeastern Minnesota, cluster randomized trial | [15] |
| HPV vaccine dose received, parent reminder-recall | 34.6% | Same trial; mailed reminder-recall after the child turned 11 or 12 | [15] |
| HPV vaccine dose received, reminder-recall plus clinician audit and feedback | 39.7% | Same trial; both interventions together | [15] |
| Targeted students reached by enhanced school-located influenza vaccination | 76.1% | 1,172 of 1,541 targeted students in 10 intervention primary schools, Beijing, 2022 to 2023 season | [3] |
| Aged care homes with at least 80% influenza vaccination coverage, 2025 | 64% | Residential aged care homes in one Australian health district, up from 29% in 2024 | [4] |

Continuum of care
Where the immunization pathway breaks between reminder and recorded dose
An immunization pathway has more steps than a reminder and a shot. It runs from identifying who is due, to contacting the family, to offering an appointment or walk-in option, to giving the dose, to recording it in a registry that other providers can see. For multi-dose series, it repeats. A break at any step leaves a person counted as unprotected or, worse, assumed to be protected. Executives need to see the whole chain, because each step usually sits with a different team and a different data system.
Delivery is the first fragile handoff. In the New York City text recall, more than a quarter of messages were not delivered successfully, since only 73% reached a phone.[2] In the Denver pilot, all 686 texts were delivered, yet digital stories were viewed by only 7 caregivers.[1] A reminder that does not arrive, or is not opened, cannot move anyone to the next step. Tracking delivery and open rates is a simple way to find out where the chain breaks before blaming families for not responding.
Series completion is the second. A systematic review of pharmacist-delivered recommendations for herpes zoster vaccination included nine studies, and only one specifically assessed completion of the recombinant vaccine series.[8] Positive findings were reported for personalized outreach and pharmacist telephone follow-up aimed at series completion.[8] The strongest evidence came from a cluster randomized trial across 16 pharmacies, where automated telephone recommendations raised vaccination rates from 0.72 to 2.60%.[8]
Recording and visibility are the third. In Australian aged care homes, interview findings suggested embedded pharmacists may strengthen vaccination coordination, data monitoring and multidisciplinary collaboration.[4] Interviewees also described operational and logistical barriers and funding issues that affect sustainability.[4] When doses given in one setting do not reach the record used by another, outreach teams waste effort recalling people who are already protected.
Transitions between settings can be designed rather than left to chance. New Zealand’s register data showed pharmacist-administered influenza vaccinations for adults aged 65 and older rose from 16,042 to 96,343 between 2018 and 2021.[7] Physician-administered vaccinations held steady over the same period, at 401,840 to 426,005 a year.[7] The authors concluded that the growth in pharmacy vaccination did not negatively affect vaccinations given by traditional providers.[7] Expanding access points, in other words, need not compete with primary care when records are shared.
Figure 3
Why the pathway breaks
People
- Frontline staff lack tools for hesitant patients
- Low proactivity of school health staff
- Untrained or unsupervised community workers
Process
- Reminders sent without follow-up for series completion
- Clinician feedback without family outreach
- No defined handoff from pharmacy or school to primary care
Technology
- Text messages not delivered or not opened
- Register reporting functions too limited
- Doses given in one setting not visible in another
Environment
- Area deprivation and distance
- Social media information overload
- Temporary vaccine shortages
Policy
- Prescription requirements that slow pharmacy access
- Unstable funding for embedded pharmacists
- Weak school administrator endorsement
Measurement
- Coverage not stratified by deprivation or language
- Zero-dose individuals not enumerated
- Delivery and open rates of reminders not tracked
Unranked qualitative cause-and-effect diagram for the outcome in the box: People who are due for a vaccine are not reached, not vaccinated on time, or not recorded as vaccinated Causes are assembled from the cited literature [1], [2], [3], [4], [6], [8], [10], [11], [12], [14]; categories are not weighted and their order carries no meaning.
Data note. Qualitative; no frequencies are implied.
Limitation. Causes drawn from published studies may not all apply locally; validate them with frontline teams.
Figure data (6 rows)
| Category | Causes drawn from the cited literature |
|---|---|
| People | Frontline staff lack tools for hesitant patients; Low proactivity of school health staff; Untrained or unsupervised community workers |
| Process | Reminders sent without follow-up for series completion; Clinician feedback without family outreach; No defined handoff from pharmacy or school to primary care |
| Technology | Text messages not delivered or not opened; Register reporting functions too limited; Doses given in one setting not visible in another |
| Environment | Area deprivation and distance; Social media information overload; Temporary vaccine shortages |
| Policy | Prescription requirements that slow pharmacy access; Unstable funding for embedded pharmacists; Weak school administrator endorsement |
| Measurement | Coverage not stratified by deprivation or language; Zero-dose individuals not enumerated; Delivery and open rates of reminders not tracked |
Access
Schools, pharmacies and mobile outreach widen the front door
Schools reach children where they already are. A mixed-methods evaluation of enhanced school-located influenza vaccination in Beijing covered 10 intervention primary schools.[3] The enhanced strategies reached 1,172 of 1,541 targeted students, an intervention coverage rate of 76.1%.[3] Around 83.3% of school implementers and 70.4% of parents favored maintaining the program.[3]
School programs still have limits. The Beijing evaluation found the strategies may have had limited success in reaching families with social media information overload or vaccine hesitancy.[3] Insufficient priority from school administrators, low proactivity among school doctors and temporary vaccine shortages also constrained implementation.[3] Health systems that partner with schools can plan for those barriers rather than discover them in the middle of a season. Shared consent processes, supply agreements and a named school contact are practical places to start.
Pharmacies extend access for adults and, increasingly, for children. A meta-analysis included 35 studies with more than 1.3 million participants.[5] In case-control analyses, people exposed to pharmacist interventions were almost five times more likely to be vaccinated, with an odds ratio of 4.87.[5] Multicomponent strategies and direct administration by pharmacists produced the most consistent improvements.[5] The most effective approaches built eligibility assessment, administration and documentation into routine workflows.[5]
Policy rules shape whether that access is usable. Across 28 U.S. jurisdictions in the 2024 to 2025 season, mean infant RSV immunoprophylaxis coverage was 35%, with no statistically significant difference by pharmacist immunization authority category.[6] Jurisdictions requiring a patient-specific prescription had lower uptake than those with independent or no authority.[6] The authors suggested that additional prescribing steps may limit timely access.[6] Health system leaders can review whether their own standing orders and protocols create similar extra steps for pharmacy partners.
Mobile outreach reaches people who cannot easily come in. A meta-analysis of vaccination interventions for Indigenous and hard-to-reach populations in Latin America and the Caribbean found that people receiving interventions were 64% more likely to achieve complete vaccination.[11] Community health worker outreach and mobile units showed the largest effects.[11] In New Mexico, mobile clinics and a helpline coincided with a statewide 55% increase in MMR vaccine doses administered compared with the same period in 2024.[13] Leaders can map where their own mobile and community-based capacity sits today, and how quickly it could be redirected to a neighborhood with a coverage gap.
Executive guidance · System route
Connect the month to an accountable system route.
Use this route as a discussion framework. Replace each stage with the organization’s approved process, qualified roles, current service capacity, and applicable requirements. Do not infer a clinical protocol from the observance title.
The route at a glance
- Identify the concern
- Activate prevention
- Align prevention and response
- Escalate and respond
- Review and improve
Reliability rule: Every stage needs a named owner, an observable status, an approved escalation path, and a defined signal that shows whether responsibility moved or remained unresolved.
Identify the concern
Define approved ways to recognize and report a concern without asking unqualified staff to make clinical or legal determinations.
Activate prevention
Make locally approved controls, tools, education, and responsibilities visible where the work occurs.
Align prevention and response
Connect approved prevention communication, qualified response, escalation, documentation, and partner coordination under local policy and applicable requirements.
Escalate and respond
Route the concern to the qualified owner, acknowledge receipt, and preserve visibility until the next action is accepted.
Review and improve
Examine exceptions, near misses, workarounds, and delays using a learning approach and transparent action ownership.
Figure 2
The system route as one flow
The five stages of the system route described in this brief, drawn as one flow with a learning loop back to the start. The stages are the page’s original executive guidance, not a clinical protocol.
Data note. Shows sequence and handoffs only; it carries no counts or rates.
Limitation. Local processes may add, merge or reorder stages under organizational policy.
Figure data (5 rows)
| Stage | What the stage requires |
|---|---|
| Identify the concern | Define approved ways to recognize and report a concern without asking unqualified staff to make clinical or legal determinations. |
| Activate prevention | Make locally approved controls, tools, education, and responsibilities visible where the work occurs. |
| Align prevention and response | Connect approved prevention communication, qualified response, escalation, documentation, and partner coordination under local policy and applicable requirements. |
| Escalate and respond | Route the concern to the qualified owner, acknowledge receipt, and preserve visibility until the next action is accepted. |
| Review and improve | Examine exceptions, near misses, workarounds, and delays using a learning approach and transparent action ownership. |
Equity and trust
Coverage gaps follow deprivation, distance and trust
Standard tools can leave the most disadvantaged children behind. The secondary analysis of the Minnesota HPV trial included 6,232 children aged 11 to 12 years.[14] Under usual care, vaccine initiation and completion were significantly lower with each increasing quartile of area deprivation.[14] The multilevel intervention increased vaccination for most children but had limited effect for those in the areas of highest deprivation.[14]
Culturally centered approaches show promise but need better reach. The Denver pilot trial took place in 2 safety-net clinics in historically Black neighborhoods, and its digital stories featured caregivers who identified as Black or African American.[1] Vaccination improved among intervention children, but reach was low, so the design is promising rather than proven.[1] Leaders can treat such pilots as a starting point for co-design with community members. That includes testing which channel, language and messenger each community prefers, and measuring reach as carefully as vaccination itself.
Community trust and leadership appear repeatedly as success factors. In the Latin American and Caribbean meta-analysis, effects were stronger for Indigenous populations, with a risk ratio of 1.85, than for other rural groups.[11] Feasibility was highest for community health worker and culturally adapted strategies because of community trust, low costs and adaptability.[11] The authors concluded that interventions integrating community health worker networks and Indigenous leadership significantly improve coverage.[11]
Equity also depends on who is counted. In southern Madagascar, local volunteer workers had lacked training and supervision, which left population data incomplete and microplanning weak.[12] Enumeration with simple digital tools and transparent incentive payments made zero-dose children visible, and 42,700 of them had received a first diphtheria-tetanus-pertussis dose by March 2026.[12] In U.S. terms, the equivalent is a registry that can find the children and adults who have never been reached.
Pharmacies are trusted, but trust varies by service. In a survey of 405 adults at a science museum, 48.4% had received a vaccination at a pharmacy.[9] Yet only 20.3% had a preferred pharmacist with whom they had an established relationship.[9] Health systems that rely on pharmacy partners for equity can strengthen those relationships deliberately, especially in neighborhoods with fewer primary care options. Shared outreach lists and referral routes between clinics and pharmacies are one way to do that.
Human infrastructure
The immunization workforce extends well beyond the clinic
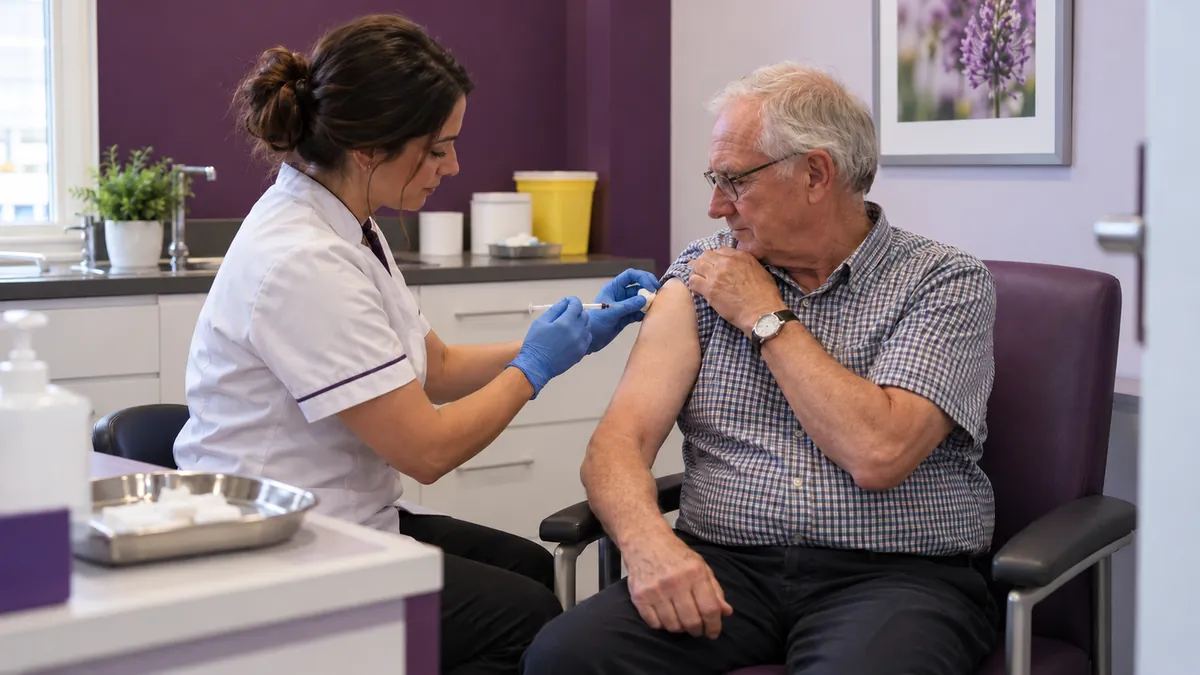
Immunization depends on a wide cast: clinicians, nurses, pharmacists, school staff, community health workers and the registry teams behind them. The research shows each group needs clear roles and support. In Australian aged care, interviews with 10 managers and 12 pharmacist immunizers identified partnerships, workflow, logistics, data access and funding as the key themes.[4] The authors stated that sustainable funding, role clarity and improved data systems are essential to maintain coverage gains.[4]
Pharmacists want better tools for difficult conversations. A qualitative study interviewed 12 community, 7 aged care and 3 general practice pharmacist immunizers across metropolitan, regional and rural Australia.[10] Pharmacists, especially in regional areas, were known to the community and offered valued advice and accessible vaccinations.[10] They identified a need for clinical guidance, scenario-based training and tools to address misinformation and emotional concerns.[10]
Those same pharmacists asked for resources suited to particular audiences. They described a need for tailored support for aged care and accessible materials for older adults, culturally and linguistically diverse communities and people with limited literacy.[10] Rural and sole pharmacists asked for peer forums.[10] Health systems that partner with community pharmacies can share their own patient education materials and clinical escalation routes. Joint training sessions can also give pharmacists and clinic staff a consistent way to answer common questions.
Clinician feedback works best alongside family-facing outreach. In the Minnesota trial, confidential audit and feedback on each clinician’s own HPV vaccination success did not significantly change uptake on its own.[15] Combined with parent reminder-recall, it produced the highest odds of vaccination.[15] For executives, that argues for pairing performance data with an operational outreach process rather than expecting reports alone to change practice.
Community health workers are the backbone of outreach in many settings. Madagascar’s initiative recruited and trained 3,975 community health workers to verify vaccination status.[12] The authors credited locally led partnerships, community health worker engagement, simple digital tools and transparent financial mechanisms for producing actionable data.[12] In the Latin American and Caribbean review, community health worker outreach was the most common intervention type, used in 43% of included studies.[11] Workforce plans for immunization can therefore count community health workers and outreach staff alongside clinicians.
Executive guidance · Operating dashboard
Review reliability, not campaign activity alone.
Do not publish a number until the organization defines its numerator, denominator where relevant, owner, source system, exclusions, review cadence, and limits. The candidates below are management prompts, not benchmarks or reported results.
Four operating signals
Each signal pairs an executive question with one candidate local measure, set out below.
Executive guidance · Signal
Prevention reliability
Are approved preventive steps usable and consistently supported in the real work environment?
- Candidate local measure
- Locally defined control checks, barriers, exceptions, and corrective-action status.
Executive guidance · Signal
Readiness
Can the right team, tool, information, and backup be reached when needed?
- Candidate local measure
- Readiness checks, unavailable resources, response barriers, and escalations.
Executive guidance · Signal
Prevention-to-response reliability
Do approved prevention messages connect to real response capacity and named ownership?
- Candidate local measure
- Locally defined readiness barriers, unowned inquiries, unresolved escalations, process exceptions, and corrective actions.
Executive guidance · Signal
Learning system
Are recurring patterns translated into owned improvements?
- Candidate local measure
- Review completion, assigned actions, overdue actions, verified changes, and shared learning.
Figure 4
The operating system behind the dashboard
The four operating signals from this brief’s dashboard, each tied to the candidate owner named in the executive scorecard, around one accountable route. Drawn from the page’s original executive guidance.
Data note. Structural diagram; no measured values.
Limitation. Owners are candidates to be confirmed locally.
Figure data (4 rows)
| Operating signal | Candidate owner |
|---|---|
| Prevention reliability | Executive sponsor and operational lead |
| Readiness | Operational owner and participating teams |
| Prevention-to-response reliability | Sending and receiving owners |
| Learning system | Improvement owner and executive sponsor |
Executive guidance · Handoff workflow
Transfer responsibility with acknowledgment and visibility.
A handoff is reliable only when the sending party knows who is expected to receive the work, the receiving party acknowledges responsibility, and any unresolved exception remains visible. Local policy and qualified judgment control the actual process.
How responsibility moves
Lane A
From message to accepted ownership
- Confirm the approved message and intended audience.
- Publish the actual entry point and receiving role.
- Acknowledge receipt using the locally approved method.
- Escalate when ownership or response remains unclear.
Lane B
From accepted ownership to verified follow-through
- Record the next accountable owner and visible status.
- Transfer concerns to the locally designated qualified owner and preserve visibility through acknowledgment.
- Keep unresolved work visible across boundaries.
- Confirm closure or document the continuing exception.
Executive guidance · Executive scorecard
Connect operating signals to accountable executive review.
The scorecard keeps review focused on decisions. Leaders should set definitions locally, examine variation without overclaiming cause, and pair quantitative signals with the experience of people who use and operate the route.
Who reviews what
- Executive sponsor and operational lead
- Operational owner and participating teams
- Sending and receiving owners
- Improvement owner and executive sponsor
Candidate owners named in the scorecard, confirmed locally.
| Operating signal | Executive question | Candidate owner | Suggested review point |
|---|---|---|---|
| Prevention reliability | Are approved preventive steps usable and consistently supported in the real work environment? | Executive sponsor and operational lead | At campaign launch and close |
| Readiness | Can the right team, tool, information, and backup be reached when needed? | Operational owner and participating teams | At a locally defined cadence |
| Prevention-to-response reliability | Do approved prevention messages connect to real response capacity and named ownership? | Sending and receiving owners | At a locally defined cadence |
| Learning system | Are recurring patterns translated into owned improvements? | Improvement owner and executive sponsor | Until action is verified |
Figure 5
Control points for a reliable immunization system
| Control point | Risk if missing | Owner | Evidence of control |
|---|---|---|---|
| Registry-based identification of everyone due or overdue | Unvaccinated people stay invisible | Ambulatory quality lead with registry or health information manager | Share of patients with a current due-or-overdue status in the registry |
| Reminder-recall with delivery and response tracking | Messages fail silently | Population health director | Delivery rate, open rate and vaccination within a set window after recall |
| Paired clinician feedback and family outreach | Reports alone do not change uptake | Chief medical officer with primary care leadership | Clinician-level rates reviewed alongside outreach completion |
| Series completion follow-up | People start but do not finish multi-dose series | Nurse manager for immunization services | Completion within the recommended interval |
| Partner dose reporting from pharmacies, schools and mobile clinics | Duplicate outreach and false gaps | Community partnerships director | Share of partner doses visible in the registry within a set time |
| Coverage stratified by deprivation, race, ethnicity, language and age | Standard tools leave disadvantaged groups behind | Chief health equity officer | Quarterly stratified coverage with named actions for the largest gaps |
| Outbreak surge plan with helpline and mobile clinics | Slow response when cases appear | Emergency management lead with public health partners | Tested plan with named staff and sites |
Control points derived from the cited evidence [1], [2], [3], [4], [5], [8], [12], [14], [15] and this brief’s executive guidance.
Data note. Each row is a control to verify, not a measured result.
Limitation. Owners and evidence of control must follow local policy and applicable requirements.
Public communication
Communicating about vaccines in ways people can act on
Public messages during National Immunization Awareness Month work best when they point to a real, nearby next step. New Mexico paired a centralized webpage with a telephone helpline and mobile vaccination clinics across a geographically large, rural state.[13] The authors concluded that coordinating public communication and improving access to MMR vaccine can support vaccine administration across large rural areas.[13] Messages without an access route ask people to solve the logistics alone. Every public message can name where to go, when the site is open, what it costs and who to call with questions.
Generic messages produce modest effects. The New York City text read simply that the Health Department recommends an annual flu shot and asked parents to call their doctor.[2] It produced a statistically significant but small relative increase among younger children.[2] Narrative messages featuring community voices were associated with better vaccination in the Denver pilot, although few caregivers opened them.[1] Testing message content with the families who will receive it is a low-cost step that many organizations skip.
Conversations still matter more than broadcasts for hesitant people. Australian pharmacist immunizers reported that supportive vaccine conversations are key to uptake but can be difficult, especially with hesitant patients.[10] The Beijing school evaluation found that entrenched parental views and social media information overload limited reach.[3] Communication plans can include training and scripts for frontline staff, not only public advertising.
Trust in the messenger shapes what people accept. In the public survey, comfort with pharmacist prescribing was high for seasonal illnesses, at 91.2%, and more moderate for chronic conditions, at 52.5%.[9] The authors concluded that most respondents view pharmacists as trustworthy professionals, although trust varies by service.[9] Organizations can match messengers to the decision being asked of the public. A trusted local pharmacist, school nurse or community health worker may be more persuasive than a system-wide advertisement.
The executive role is to make communication part of the operating design. That means confirming that reminders are delivered and opened, that each message names a real place and time, and that staff have the training to answer questions. It also means reporting coverage openly, including the neighborhoods and age groups the organization has not yet reached. The evidence in this brief suggests those are the points where awareness becomes a recorded dose.

Executive guidance · 90-day plan
Use 90 days to correct one visible operating barrier.
The time boxes below are a management framework, not a clinical timeline. Adjust them to risk, scope, governance, resources, stakeholder participation, and applicable review requirements.
Ninety days, three moves
- Days 1–30See the current route
- Days 31–60Build the reliable path
- Days 61–90Make the change visible
Days 1–30 · Listen and map
See the current route
- Name an executive sponsor and an operational owner.
- Listen to people using the route and representative frontline teams.
- Map how National Immunization Awareness Month communications connect to real entry points, owners, transitions, and escalation.
- Select one recurring barrier that the organization can responsibly address.
Days 31–60 · Design and test
Build the reliable path
- Define the trigger, receiving owner, required information, acknowledgment, escalation, and closure signal.
- Validate the design with every sending and receiving team involved.
- Test one prevention-to-response route against local policy and correct a verified readiness or ownership gap.
- Test the route in more than one representative setting or operating period where practical.
Days 61–90 · Implement and verify
Make the change visible
- Launch the redesigned route with a small set of locally defined measures.
- Review unresolved work and recurring friction using a learning approach.
- Correct implementation barriers and record who owns each remaining dependency.
- Report what changed, what evidence was reviewed, and what still requires live oversight.
Figure 6
The 90-day plan on one timeline
The 90-day plan from this brief drawn as a timeline: each action sits in the 30-day window the plan assigns it. The full wording of each action is in the figure data and in the plan above.
Data note. Time boxes are a management framework, not a clinical timeline.
Limitation. Durations are uniform 30-day windows; real tasks may span windows.
Figure data (12 rows)
| Window | Action |
|---|---|
| Days 1–30 · Listen and map | Name an executive sponsor and an operational owner. |
| Days 1–30 · Listen and map | Listen to people using the route and representative frontline teams. |
| Days 1–30 · Listen and map | Map how National Immunization Awareness Month communications connect to real entry points, owners, transitions, and escalation. |
| Days 1–30 · Listen and map | Select one recurring barrier that the organization can responsibly address. |
| Days 31–60 · Design and test | Define the trigger, receiving owner, required information, acknowledgment, escalation, and closure signal. |
| Days 31–60 · Design and test | Validate the design with every sending and receiving team involved. |
| Days 31–60 · Design and test | Test one prevention-to-response route against local policy and correct a verified readiness or ownership gap. |
| Days 31–60 · Design and test | Test the route in more than one representative setting or operating period where practical. |
| Days 61–90 · Implement and verify | Launch the redesigned route with a small set of locally defined measures. |
| Days 61–90 · Implement and verify | Review unresolved work and recurring friction using a learning approach. |
| Days 61–90 · Implement and verify | Correct implementation barriers and record who owns each remaining dependency. |
| Days 61–90 · Implement and verify | Report what changed, what evidence was reviewed, and what still requires live oversight. |
Executive guidance · Leadership close
Pair recognition with a system people can trust.
Recognition matters. It becomes durable when leaders also listen, clarify the route, support the people operating it, close an identified gap, and report the result without claiming more than the evidence supports.
Leadership commitment
Connect the message to one usable, measured, and sustained operating change.
Executive action kit · Month observance
Turn National Immunization Awareness Month into accountable action.
Move beyond reminders by reviewing how the organization prevents, detects, responds, and learns.
Leadership focus
Use this observance to examine trustworthy information, prevention access, and community connection. Select one verified barrier, assign an accountable owner, and carry the improvement beyond the campaign window.
Workforce lens
Ask whether staffing, role clarity, training, tools, workload, and escalation support the people operating the information, prevention, readiness, and response pathway.
Patient and community lens
Make the approved first step clear. Test whether a person can move from information to an acknowledged next action without navigating conflicting instructions.
Equity and access lens
Review language access, digital access, transportation, trust, and other barriers that may affect prevention information or connection to approved services.
Five-minute briefing
Inspect the operating sequence
Listen with infection prevention, clinical teams, operations, communications, and community-facing partners. Find one conflicting guidance, unclear entry points, or delayed escalation, then test the locally approved route from entry through acknowledged follow-through.
- Identify the concern
- Activate prevention
- Align prevention and response
- Escalate and respond
- Review and improve
Leadership actions for this week
- Name an executive sponsor and frontline operating owner.
- Ask people using and operating the pathway where ownership becomes unclear.
- Test one representative route from first question to acknowledged next step.
- Select one barrier that can be corrected without overstating the evidence.
- Set a review date and define how completion will be verified.
Candidate measures
Define every numerator, denominator where relevant, owner, data source, exclusions, cadence, and limitation locally. These are management prompts, not external benchmarks.
- Locally defined control checks, barriers, exceptions, and corrective-action status.
- Readiness checks, unavailable resources, response barriers, and escalations.
- Locally defined readiness barriers, unowned inquiries, unresolved escalations, process exceptions, and corrective actions.
Department readiness checklist
- The public and staff entry points match the actual approved process.
- A specific role accepts each request, referral, or escalation.
- Handoffs include acknowledgment and a visible unresolved state.
- Language, disability, digital, transportation, and trust barriers receive explicit review.
- Communications do not introduce unsupported themes, statistics, or clinical advice.
- A named leader will review what changed after the observance.
Intended audiences
- Executive and Operational Leaders
- Public Health and Community Partners
Staff communication template
During National Immunization Awareness Month, our organization will connect awareness with a practical review of the information, prevention, readiness, and response pathway. Use approved information, identify the correct entry point, confirm ownership when work moves, protect privacy, and escalate unresolved barriers through local channels.
Community communication template
National Immunization Awareness Month is an opportunity to share trustworthy information and make the next step easier to find. Use our approved channels for information and support. If a request changes hands, our goal is to keep ownership and follow-through visible.
Measurement worksheet
- Signal
- What observable condition will show whether the route works?
- Definition
- What is included, excluded, and counted?
- Owner
- Who reviews the signal and acts on exceptions?
- Cadence
- When will leaders review it?
- Equity check
- Which differences require protected, locally appropriate review?
- Closure
- What evidence will confirm the improvement was completed?
- Editorial review
- Completed
- Source records
- 2 listed under Authoritative resources
- Review standard
- Sourced facts remain separated from original executive guidance
- Clinical boundary
- No new statistical or clinical claim was added by this action kit
Sources and content boundary
Authoritative resources
Use note: All operating models, measures, scorecard questions, and action steps are original executive guidance. This article supports leadership planning and education. It does not replace clinical judgment, emergency procedures, legal advice, professional standards, organizational policy, or applicable federal, state, and local requirements.
Peer-reviewed references
References
Fifteen peer-reviewed sources, newest first. Each was individually verified through authenticated academic research databases. Bracketed numbers in the text link here; the original executive guidance on this page carries no citations because it is guidance, not a sourced claim. Sources last checked in those databases on .
- 1.Williams JTB, Kurlandsky K, Stein AB, Bharadwaj N, Hambidge SJ, Pereira RI, et al. Narrative Reminder Recall to Improve Pediatric Influenza Vaccination: a Pilot Randomized Clinical Trial. JAMA Network Open. 2026;9(1):e2552149-e2552149. https://doi.org/10.1001/jamanetworkopen.2025.52149
- 2.Cheng I, Papadouka V, Ternier A, Langdon-Embry M, Daskalakis DC, Zucker JR. A Centralized Text Message Recall for Pediatric Influenza Vaccination, New York City, 2017. Journal of Public Health Management and Practice. 2026;32(5):E211-E218. https://doi.org/10.1097/phh.0000000000002380
- 3.Hu Y, Yan R, Yin X, Gong E, Wang Y, Xin X, et al. Implementation of Multifaceted Enhanced School-located Influenza Vaccination Strategies in China: A Mixed Methods Evaluation Using the RE-AIM Framework and Normalization Process Theory. International Journal of Behavioral Medicine. 2026:1-13. https://doi.org/10.1007/s12529-026-10452-8
- 4.White J, Vidler M, Murray P, Fairjones A, Wallace B, Hullick C, et al. Integrating Pharmacists Into Aged Care Vaccination: Strengthening Public Health Immunisation Systems Through the Aged Care on‐Site Pharmacist Program (ACOP) in Australia. Australasian Journal on Ageing. 2026;45(3):1-9. https://doi.org/10.1111/ajag.70223
- 5.Borlini S, Pennisi F, Pinto A, De Ponti E, D’Amelio AC, Signorelli C. Impact of pharmacy-based interventions on vaccination coverage among vulnerable and underserved populations: a systematic review and meta-analysis. Vaccine. 2026;78. https://doi.org/10.1016/j.vaccine.2026.128426
- 6.Steverson C, Saiar A, Daniels R, LaNou E. Impact of pharmacist immunization authority on infant respiratory syncytial virus immunoprophylaxis rates. JAPhA Practice Innovations. 2026;3(3). https://doi.org/10.1016/j.japhpi.2026.100091
- 7.Larson A, Mitrovich R, Musse I, Lansdale AJ, Eiden AL. Expanding the role of pharmacists as vaccinators in New Zealand: a retrospective analysis of influenza vaccination trends following policy change. International Journal of Pharmacy Practice. 2026:1. https://doi.org/10.1093/ijpp/riag102
- 8.Kuczwalska E, Dworakowska AM, Skarżyńska M, Bujalska-Zadrożny M. Effectiveness of pharmacist-delivered vaccination recommendations for herpes zoster: a systematic review. Frontiers in Public Health. 2026;14:1884479. https://doi.org/10.3389/fpubh.2026.1884479
- 9.Michel D, Murphy EM, Shaw Ojeda M, Hill EG. Pharmacists through a public lens: Understanding trust, role recognition, and support for prescribing. Research in Social and Administrative Pharmacy. 2026;22(12):1162-1168. https://doi.org/10.1016/j.sapharm.2026.07.010
- 10.Bolsewicz KT, Steffens MS, Cox LS, Hazelwood E, Andreatta J, Bae Y, et al. Australian pharmacist immunisers in vaccine conversations with patients: a qualitative study to explore communication support needs. Journal of Pharmaceutical Policy and Practice. 2026;19(1):2694236. https://doi.org/10.1080/20523211.2026.2694236
- 11.Husaini DC, Morales S, Hung JC, Eck L. Effectiveness and feasibility of vaccination interventions for Indigenous and hard-to-reach populations in Latin America and the Caribbean: a systematic review and meta-analysis. Therapeutic Advances in Vaccines and Immunotherapy. 2026;14:1-18. https://doi.org/10.1177/25151355261472591
- 12.Muller N, Mahafeno AF, Rasolofondraibe AC, Andriantiantsoa GT, Randrianirisoa ANS, Ramarosaiky E, et al. Identification of unvaccinated children, Madagascar. Bulletin of the World Health Organization. 2026;104(8):560-565. https://doi.org/10.2471/blt.25.295299
- 13.Stanislawski E, Romero A, Holzinger N, Healy R, Webb NJ, Cruz K, et al. Measles Outbreak - New Mexico, 2025. Morbidity and Mortality Weekly Report. 2026;75(9):111-115. https://doi.org/10.15585/mmwr.mm7509a1
- 14.Kong WY, Finney Rutten LJ, Herrin J, St Sauver JL, Jenkins GD, Griffin JM, et al. Multilevel Intervention and Human Papillomavirus Vaccination Disparities: a Secondary Analysis of a Cluster Randomized Trial. JAMA Network Open. 2025;8(7):e2518895-e2518895. https://doi.org/10.1001/jamanetworkopen.2025.18895
- 15.Finney Rutten LJ, Griffin JM, St Sauver JL, MacLaughlin K, Austin JD, Jenkins G, et al. Multilevel Implementation Strategies for Adolescent Human Papillomavirus Vaccine Uptake: a Cluster Randomized Clinical Trial. JAMA Pediatrics. 2024;178(1):29-36. https://doi.org/10.1001/jamapediatrics.2023.4932
Claim-to-source matrix
What each source supports
Every sourced claim in the new sections maps to the references that support it, the section where it is used, and the limitation a reader should keep in mind. Original executive guidance carries no sources because it is guidance, not a finding.
| Claim group | Sources | Years | Used in | Limitation |
|---|---|---|---|---|
| Reminder-recall and audit-feedback effects on HPV vaccination | [15] [14] | 2025, 2024 | Current evidence | Six primary care practices in one Minnesota system; mostly White, urban population. |
| Registry-based and narrative text message recall for influenza vaccination | [2] [1] | 2026 | Current evidence | Small effect in a 2017 citywide trial; small pilot trial with low reach in two clinics. |
| Coverage measurement and zero-dose identification | [12] [4] | 2026 | Current evidence | Program report from southern Madagascar; Australian register data where attribution to one program was not possible. |
| Series completion and telephone outreach | [8] | 2026 | Continuum of care | Mostly non-randomized studies with serious risk of bias; only one randomized trial. |
| Pharmacy vaccination growth alongside traditional providers | [7] [5] | 2026 | Continuum of care | Descriptive New Zealand register trends; meta-analysis of heterogeneous studies. |
| School-located vaccination reach and implementation barriers | [3] | 2026 | Access | Ten intervention schools in Beijing during one season. |
| Pharmacist authority and access to infant RSV prophylaxis | [6] | 2026 | Access | Ecological comparison of 28 jurisdictions early in product rollout. |
| Community health worker, mobile and culturally adapted outreach | [11] [13] | 2026 | Equity and trust | Latin American and Caribbean studies of variable quality; New Mexico increase coincided with but was not attributed to outreach. |
| Pharmacist communication needs and public trust in pharmacists | [10] [9] | 2026 | Human infrastructure | Qualitative Australian interviews; single-site convenience survey. |
About the author
Greg Wahlstrom
MBAHCM
President and Chief Executive Officer, The Healthcare Executive
View Greg’s profile©2014 – 2026 The Healthcare Executive. All rights reserved.